Home | Log out
Showing posts with label Clomid. Show all posts

Friday, September 18, 2009

South Texas women needed for infertility study

Friday, September 18, 2009
UTHSC needs volunteers for infertility study - Women with PCOS will test two different medications to help them get pregnantSouth Texas patients are helping to compare two oral drugs to boost fertility: a commonly-used pill called Clomid and a newer pill called Letrozole first used for breast cancer patients. Both lead to stimulation of egg growth, but they work in different ways.

“Because they work through different mechanisms, we’re hopeful that maybe certain women will benefit from one versus the other, or maybe all women will benefit from the new medication,” Brzyski explained. “There’s always that great hope.”

Women between the age of 18 and 40 who have eight or fewer periods per year are eligible to be screened for this study. For more information, contact the study coordinator at UTHSC, Carann Easton, R.N., at (210) 567-6245 or eastonc@uthscsa.edu .

Read more: http://www.kens5.com/news/health/stories/KENS20090911-PolycysticOvaryStudy.16dc48945.html

Life Begins... - Miscarriage stories of loss, hope & help
Pregnancy Stories by Age - Daily blog of hope & inspiration!
Stories of Pregnancy over 44 years old - sharing stories I find online, for inspiration!


Recent Keyword Searches: having a child at 42, how to make an older woman pregnant, 46 years old want to be pregnant,inhibin b, can you get pregnant aftr 50, can you get in vitro at age 42

read more

Saturday, April 25, 2009

Male Infertility Treatment Boosts Sperm Count

Saturday, April 25, 2009
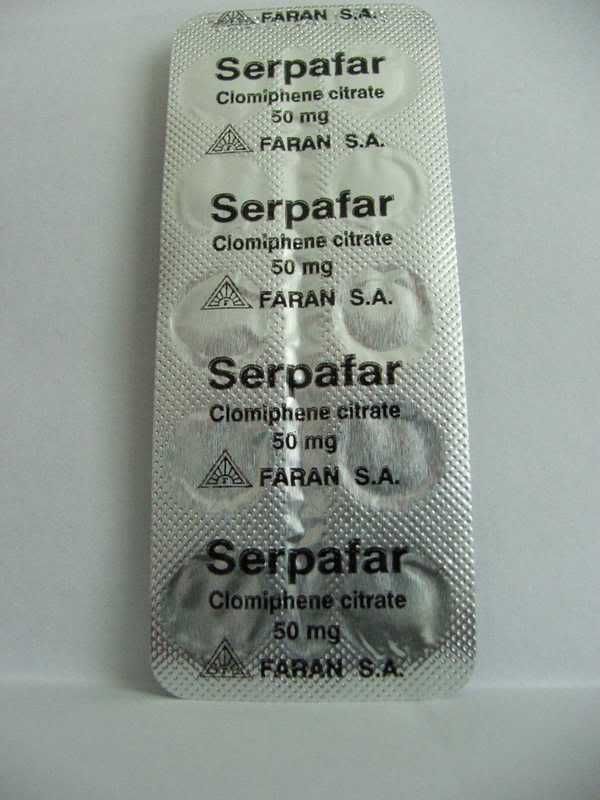
clomiphene citrateMONDAY, April 6 (HealthDay News) -- A hormone-antioxidant combination therapy appears to improve sperm count and motility in infertile men, according to an Egyptian study.

The research included 60 men eligible for infertility treatment. They were randomly selected to take either the combination treatment of clomiphene citrate and vitamin E or a placebo for six months. By the end of the study, their partner's pregnancy rate was about 37 percent among men who'd taken the combination therapy, compared with 13 percent for those in the placebo group.

Read more:
http://www.forbes.com/feeds/hscout/2009/04/06/hscout625605.html


Life Begins...
Miscarriage stories of loss, hope & help
http://born2luv.blogspot.com/

Stories of Pregnancy & Birth over 44y
- Daily blog of hope & inspiration!
http://pregnancyover44y.blogspot.com/

5,000 Stories of Pregnancy & Birth over 44y
Daily blog of hope & inspiration!
http://pregnancyover44y.blogspot.com/


Recent Keyword Searches: predictability of 39 year old female getting pregnant, can low estrogen getting pregnant, can increase levels of estrogen decrease chances of getting pregnant, odds of getting pregnant at 42, articles about menopausal baby

read more

Saturday, October 18, 2008

Am I more likely to get pregnant if I take a fertility drug such as Clomid?

Saturday, October 18, 2008
Picture by newbuilderuk
Am I more likely to get pregnant if I take a fertility drug such as ClomidNo, at least not if you take it alone, without other interventions, according to a new study by Scottish researchers in the British Medical Journal.

Neither
Clomid (clomiphene citrate) - which is an ovulation stimulator - nor artificially inseminating women with sperm injected directly in the uterus, resulted in more live births than simply continuing to try to have babies the old-fashioned way, concluded the study. It was led by Siladitya Bhattacharya, a professor of reproductive medicine at the University of Aberdeen.

The study involved nearly 600 women who were unable to conceive for more than two years. These women had normal
ovulatory cycles, open and healthy fallopian tubes and their partners had normally functioning sperm.

Full story: http://www.boston.com/news/health/articles/2008/10/13/am_i_more_likely_to_get_pregnant_if_i_take_a_fertility_drug_such_as_clomid/


Life Begins...
Miscarriage stories of loss, hope & help
http://born2luv.blogspot.com

Stories of Pregnancy & Birth over 44y
- Daily blog of hope & inspiration!
http://pregnancyover44y.blogspot.com

4,800 Stories of Pregnancy & Birth over 44y
Daily blog of hope & inspiration!
http://pregnancyover44y.blogspot.com/


Recent Keyword Searches: ivf high fsh 38 pregnant, how common is it to get pregnant naturally in middle forties, retrieve eggs over 40 and pregnant, too old to get pregnant 45, what can i do to get pregnant at 40yrs

read more

Saturday, August 16, 2008

Clomid, IUI no help for some types of infertility

Saturday, August 16, 2008
Photo by news.bbc.co.uk
Clomid, IUI no help for some types of infertilityA new study suggests that using the medication Clomid and undergoing intrauterine insemination (IUI) offer no benefit to women who suffer from unexplained infertility.

Researchers point out that many doctors use both of these methods on women who show no obvious reason for their infertility because "doing nothing" is not popular.

But in a study of 580 women, those who used Clomid or underwent IUI were no more likely to get pregnant than if they had done nothing. Experts point out that both Clomid and IUI are highly useful, but only if women have trouble ovulating or if there is a sperm motility issue.

(BBC News) UPDATED 08/08/2008
Click here to read the full story


Life Begins...
Miscarriage stories of loss, hope & help
http://born2luv.blogspot.com/

Stories of Pregnancy & Birth over 44y
- Daily blog of hope & inspiration!
http://pregnancyover44y.blogspot.com/

4,750 Stories of Pregnancy & Birth over 44y
Daily blog of hope & inspiration!
http://pregnancyover44y.blogspot.com/


Recent Keyword Searches: can i get pregnant over the age of 45 without help, risks of having a baby at 44, can a woman still get pregnant with old ovaries, getting pregnant in your 40, can i get pregnant at 44 yrs old?

read more

Sunday, January 27, 2008

Baby, baby: Two women share their experiences with fertility drugs

Sunday, January 27, 2008
Amy and Stephen Smyk of Vestal tried unsuccessfully to start a family for more than seven years.

"We went through batteries of tests," said Smyk, now 38. "There was no reason why we couldn't get pregnant."

So they turned to fertility drugs for help. Within two months, Smyk was pregnant with Kara, now 3. The drugs also helped her to conceive Hannah, who turns 9 months old this week.

"Without this help, I don't know if we could have had healthy pregnancies," said Smyk, who described her daughters as a "complete and utter blessing."

Cost of treatment

The Smyks are among an estimated 10 percent of couples across the United States who have difficulty conceiving children. About 5 to 7 percent of them turn to fertility treatments for help, said Dr. James Kondrup, a Vestal gynecologist who treated Amy Smyk.

Locally, numbers of couples seeking fertility treatments have dropped from a high of 15 patients per week back in the early 1990s to four or five patients per week. That's due to the loss of jobs suffered by the Southern Tier and cutbacks in insurance coverage, Kondrup said.

"Patients cannot afford to pay for fertility treatments out of their pocket," said Kondrup, who's been practicing in Broome County for 20 years.

Treatments range from $50 for one cycle of five pills (the most common option being Clomid) to $2,000 for one cycle of injectable treatments, called gonadotropins, he said. Some insurance companies cover the cost of treatments while others don't. Smyk's insurance covered two rounds of injections -- enough time to help her conceive.

Seeing double

One of the side effects of using fertility drugs is multiple-birth pregnancies -- which Beth Wolfer of Berkshire experienced after injecting fertility treatments. Evan and Larissa will turn 3 years old in March.

The chances of having twins increases by 5 to 10 percent if a woman takes Clomid, according to the Centers for Disease Control and Prevention. It's extremely rare -- almost impossible -- to have triplets or more when using that drug.

Women who use gonadotropins see their chances of having twins rise to 15 to 20 percent, and there's a 5 percent chance of having triplets or more with the injectable form, the CDC reports.

Either way, multiple births have a higher chance of complications such as low birth weight -- which occurs in 5 to 10 percent of pregnancies. Evan weighed just 1 pound, 7 ounces while Larissa weighed 1 pound, 4 ounces when they were born prematurely.

"There were times we didn't know if we they were going to make it," Wolfer said of herself and her husband, Matthew.Today, the twins are doing well with the help of speech, physical and occupational therapy, she said.

Is it worth it?

Both Smyk and Wolfer say they advise any couple trying unsuccessfully to have children to try fertility treatments.

"The science is out there to do it," said Wolfer, 40. "It can work."

Both women say they don't regret all the shots, the countless trips to the doctor's office and the long wait to become a mother.

"It's a roller coaster of emotions", Wolfer said. "It's not easy. But it's all worth it."

Source: http://www.pressconnects.com/apps/pbcs.dll/article?AID=/20080127/LIFESTYLE/801270333/1004/LIFESTYLE


Life Begins...
Miscarriage stories of loss, hope & help
http://born2luv.blogspot.com/

Stories of Pregnancy & Birth over 44y
- Daily blog of hope & inspiration!
http://pregnancyover44y.blogspot.com/

4,350 Stories of Pregnancy & Birth over 44y
Daily blog of hope & inspiration!
http://pregnancyover44y.blogspot.com/

Recent Keyword Searches: risks of having a baby at 40 years old, can woman get pregnant at age 45 and higher, is it possible to get pregnant at 43?, can you get pregnant at age 55, is it easy to get pregnant at 45?, how to be pregnat when you are 50 years old ?, can you become prgenant in perimenopause, oldest woman to get pregnant, can you become pregnant at age 50?, is it possible to get prenant at age 48


read more

Tuesday, October 23, 2007

'Fast-track' IVF saves time and lowers risks

Tuesday, October 23, 2007
Fertility patients could save time and money by skipping some recommended steps in treatment and going straight to IVF, according to a new study. This would mean that couples with fertility problems would not lose precious time in conceiving a child.

Women who skipped the rounds of artificial insemination with hormone treatment, recommended in the US, and went straight to IVF became pregnant 30% faster than their counterparts following traditional US protocols. The researchers now say that doctors should abandon the use of artificial insemination combined with direct hormone treatment.

In countries such as the US, doctors recommend that women seeking fertility treatment follow a three-step process. The first part involves receiving a drug called Clomid, which boosts egg production, and then injecting sperm into the body through artificial insemination. One cycle of this treatment has a 6% to 9% success rate.

Doctors typically attempt three cycles of artificial insemination with Clomid. If this fails, they move to the next step – artificial insemination in combination with "follicle stimulating" hormone (FSH).


Dangerous pregnancies

The administration of FSH ramps up egg production far beyond Clomid, and for this reason, use of the hormone often results in dangerous triplet pregnancies. This method has an estimated success rate of 9% to 15%. If three such cycles fail to work, women receive in-vitro fertilisation (IVF) treatment as a last resort.

Because of the unpredictable risk of dangerous triplet and quadruplet pregnancies with FSH-based artificial insemination, some fertility clinics have started skipping this step and going straight to IVF if the Clomid treatment fails.

"More and more couples are skipping the middle step or going directly to IVF," says Richard Reindollar of the Dartmouth-Hitchcock Medical Center in Lebanon, New Hampshire, US. But experts have remained unsure whether this "fast-tracked" IVF is a wise move.

'No benefit'

So Reindollar and colleagues studied the outcome of 503 couples with unexplained infertility who were randomly assigned to either the three-step process or the "fast-tracked" two-step process.

They found that both groups had a similar success rate – while 185 (75%) of the couples receiving conventional treatment achieved pregnancy, 199 (78%) of those assigned to the fast-track protocol achieved pregnancy.

Moreover, the fast-track couples had a 40% better chance of achieving pregnancy in the first year of treatment than those undergoing standard treatment. And while the latter group took 11 months and $71,399 on average to produce pregnancy, this happened within eight months – 30% faster – for couples who skipped the middle step, and cost $61,553 on average.

According to Reindollar, the results show that artificial insemination combined with FSH "does not provided added benefit over an accelerated approach that eliminates this treatment".

"It pretty definitively shows that there's no benefit from this middle step," comments Evan Myers at the University of North Carolina School of Public Health in Chapel Hill, North Carolina.

Reindollar says his study – the first to prospectively investigate the impact of fast-tracked IVF – should prompt clinics to skip FSH-based artificial insemination and thereby reduce the risk of complicated triplet pregnancies. He admits that IVF can also carry an elevated risk of triplet pregnancies, but stresses that this can be avoided by transferring fewer embryos.

The findings were presented at the annual meeting of the American Society for Reproductive Medicine in Washington, DC, US on Thursday.

Source: http://www.newscientist.com/article/dn12803-fasttrack-ivf-saves-time-and-lowers-risks.html


read more

Sunday, July 29, 2007

Oopause - poor ovarian response

Sunday, July 29, 2007
One of the most frustrating problems in IVF today is that of poor ovarian response. This is also known as poor ovarian function, poor ovarian reserve, occult ovarian failure, or the oopause. It’s well known that pregnancy rates in IVF are directly dependent upon the quality and number of embryos transferred, and the more the eggs a woman grows, the better the embryos we can select from. This is why women with a good ovarian response have much higher pregnancy rates than women with a poor ovarian response.

Usually, ovarian functions goes hand in hand with age, and as a women becomes older, her ovarian response starts declining. Every girl is born with a finite number of eggs, and their number progressively declines with age. A measure of the remaining number of eggs in the ovary is called the "ovarian reserve"; and as the woman ages, her ovarian reserve gets depleted. The infertility specialist is really not interested in the woman's calendar (or chronological age), but rather her biological age - or how many eggs are left in her ovaries.

Various tests have been described to measure ovarian reserve. The commonest test measures the level of FSH ( follicle stimulating hormone) in the blood - the basal ( day 3) FSH level. A high level suggests poor ovarian reserve; and a very high level ( more than 20 mIU/ml, though this varies from lab to lab ) is diagnostic of ovarian failure. A test that can provide earlier evidence of declining ovarian function is the clomiphene citrate challenge test ( CCCT). This is similar to a " stress test " of the ovary; and involves measuring a basal Day 3 FSH level; and a Day 10 FSH level, after administering 100 mg of clomiphene citrate from Day 5 to Day 9. If the sum of the FSH levels is more than 25, then this suggests poor ovarian function, and predicts that the woman is likely to have a poor ovarian response ( she will most probably grow few eggs, of poor quality) when superovulated. Remember that a high FSH level does not mean that you cannot get pregnant - it just means that your chances are dropping because your egg quality is impaired.

Some women find it difficult to understand why FSH levels are high in women with poor quality eggs. Intuitively, more is better, so higher levels should mean better eggs, shouldn't it ? As one patient asked me, " If FSH stands for Follicle Stimulating Hormone, and I have high levels of FSH, then doesn't that mean that I have the ability to stimulate lots of follicles ? A high FSH should mean that I should have lots of eggs ! " I had to explain the basic biology to her. Normally , FSH is produced by the pituitary, and this is the hormone which is responsible for the growth of the egg from the ovary every month. In young women with lots of good quality eggs, low levels of FSH are enough to grow the eggs. However, as the woman grows older and egg quality and quantity decline, the pituitary needs to produce more and more FSH to stimulate egg growth, because the FSH has to work harder to stimulate egg growth.

Another test which has been recently developed is the measurement of the level of the hormone, inhibin B, in the blood. Low levels of inhibin B ( which are produced by " good " follicles) suggest a poor ovarian reserve. However, just because a test result is normal does not mean that the quality or number of the eggs produced will be good - the final proof of the pudding is always in the eating ! This is why one of the most useful ways of making a diagnosis of poor ovarian reserve is when the patient gives a history of responding poorly to medications used for superovulation in the past.

Along with using biochemical tests to assess ovarian function, we can use biophysical markers to test these too. These biophysical tests use ultrasound technology to image the ovaries and the follicles. The most useful test is called an antral follicle count ( AFC) , in which the doctor counts the number of antral follicles ( also referred to as resting follicles) present in the ovary on Day 3 using vaginal ultrasound scanning. Antral follicles are small follicles , usually about 2-8 mm in diameter. The number of antral follicles correlates well with ovarian response. A normal total antral count is between 15 and 30. If the count is less than 6, the prognosis is poor. You can read more about the antral follicle count and see ultrasound images of these at the www.advancedfertility.com website . The volume of the ovaries also correlates with ovarian response. The volume of each ovary is calculated using the formula ( length × width × height × 0.5 ) and the normal ovarian volume of both ovaries combined is 10 ml. Women with small ovaries ( volume of less than 4 ml) have a poor ovarian response.

While an older woman often expects to have poor ovarian reserve, and is prepared for the fact that she may respond poorly to superovulation, when a young woman finds out she is a poor ovarian responder, this comes as a rude blow. Most young women expect that their eggs will be fine, because they are young and have regular cycles, but this is not always true. Regular periods simply means that the eggs are good enough to produce enough hormones to have normal menstrual cycles; however, this does not mean that the egg quality is good enough to make a baby ! Ovarian reserve is a biological variable, and egg quantity and quality in an individual woman can be average for her age, better than average, or worse than average. Women with poor egg quality are said to have poor ovarian reserve , poor ovarian function, or occult ovarian failure; and Dr Jansen has coined the term , oopause, to describe this condition.

This diagram by Dr Norbert Gleicher illustrates the concept of a "fertility curve," which suggests there may be a "norm" for ovarian aging, and hence cases in which ovarian aging can be termed "premature."

Many women cannot understand why they will have a problem producing lots of eggs when they have regular menstrual cycles. " If I produce an egg every month, then why can't I produce a lot of eggs when you give me a lot of HMG injections for superovulation ? " I explain that just because a car goes at 10 mph when you drive it in 1st gear, this does not mean you can predict what it's speed will be when you drive it in 4th gear !

Many treatment strategies have been developed in order to treat women with poor ovarian reserve. Because time is at a premium for these women, treatment needs to be aggressive, in order to help them conceive before their eggs run out completely. IVF is usually their best option, as it offers the highest success rates. Superovulating these women can be quite tricky, and this is where the experience and the expertise of the doctor makes a critical difference ! While it is true that a skilled doctor will be able to design an optimal superovulation for women with poor ovarian reserve, it is also true that the results are still likely to be poor. While Michael Schumacher will drive your car much better than you will ever be able to, if you give him a broken-down lemon to drive , even his skills are likely to let him down !

They usually need much higher doses of gonadotropin injections ( HMG) for superovulation. We have used upto 750 IU of HMG ( 10 amp of 75 IU) daily for difficult women, in order to stimulate them to grow eggs. Unfortunately, this is like scraping the bottom of the barrel, and the quantity and quality of their eggs often still remains poor.

Recently, we have had extremely good results with the Letrozole-Antagon protocol for poor ovarian responders.

In this protocol, downregulation is not needed, and we use your own gonadotropins to improve follicular recruitment in order to help you grow more eggs.

For patient who are poor ovarian responders, we transfer all the embryos we get, to maximise the chances of implantation. In this group, the risk of a multiple pregnancy is very low.

After the transfer, luteal phase support is provided with daily Progynova ( estradiol valerate2 mg, 3 tab daily; and Uterogestan ( 200 mg), 6 vaginal suppositories daily. You can travel back 3 days after the embryo transfer.
14 days after the transfer, you need to do a blood test for beta HCG to confirm a pregnancy.

Other clinics have tried using rec FSH ( recombinant gonadotropins) or GnRH antagonists, but neither of these help. In the past, doctors tried adding growth hormone injections ( because of the “growth factors” this contained) , but this was of no use. Interestingly, some doctors have gone back to using the natural cycle, or trying gentle stimulation with clomiphene for these women, since they don’t see any benefit in spending hundreds of dollars just to get 2-3 more eggs for IVF.

Interestingly, we see a lot of women who are iatrogenic poor ovarian responders – who have a poor ovarian response because they have been badly superovulated. These are typically women who have PCOD ( polycystic ovarian disease), who are undergoing IVF in clinics which don’t have much experience with treating such patients. Because their doctors are so scared of ovarian hyperstimulation syndrome ( OHSS), in their anxiety to prevent this complication, they often trigger off ovulation and egg retrieval too early. As a result of this mis-timing of the HCG shot, most of the eggs retrieved are immature, and fail to fertilise. These woman are then labeled as being poor ovarian responders , when in reality it is their doctors who are poor ovarian stimulators ! If they are superovulated properly in a good IVF clinic, their pregnancy rates are excellent.

What happens if you are young and find that you have a poor ovarian response in the middle of your first IVF cycle ? This is a very difficult problem, because it was not anticipated, and you are not emotionally prepared to deal with it. Options include: continuing the cycle with an increased dose of injections; or canceling this cycle and starting a new cycle later with a higher dose of injections. However, the prognosis remains poor, and there is no certainty that you will grow more eggs with a higher dose the next time around.

The option which offers the highest pregnancy rate for women with a poor ovarian response is to use donor eggs. While this is medically straight forward, it can be very hard for a young woman with regular cycles to accept this option. Often, it’s worth doing one cycle with your own eggs even if the chances are poor, so that you have peace of mind that you did your best. This also may make it easier to explore the option of donor eggs for the future.

Source: http://www.drmalpani.com/oopause.htm

read more

Friday, July 20, 2007

Studies About High FSH and It's (Sometimes) Non-DOR/POF Meaning

Friday, July 20, 2007
Found on the High FSH Support board:

I was 'diagnosed' on June 5 by the first RE I went to. My husband and I were so disturbed by the High FSH (16) diagnosis that we started going through the medical literature. (I'm a trained librarian and my husband's mother is a nurse. He learned in self-defense ) Anyway, we ended up going to a completely different doctor for a second opinion - which gave us better news - with a ton of research in our hands:

Other reasons for High FSH:
http://www.ncbi.nlm.nih.gov/entrez/query.fcgi?db=pubmed&cmd=Retrieve&dopt=Abstract&list_uids=9871915&query_hl=2&itool=pubmed_docsum

Twinning:
http://www.infertilityspecialist.com/ovulation_toner.html -- this also mentions Thyroid and the writer blasts the tendency to push DE even though he runs the DE program at his clinic.

http://jcem.endojournals.org/cgi/content/full/83/2/481#T1

Cimetidine:
http://www.ncbi.nlm.nih.gov/entrez/query.fcgi?cmd=Retrieve&db=PubMed&list_uids=7946012&dopt=Abstract

Clomiphene:
http://www.ncbi.nlm.nih.gov/entrez/query.fcgi?db=pubmed&cmd=Retrieve&dopt=Abstract&list_uids=12254980&query_hl=2&itool=pubmed_DocSum

Thyroid and FSH: (Find Alec's posts for the best on Thyroid issues.)
http://www.ncbi.nlm.nih.gov/entrez/query.fcgi?cmd=Retrieve&db=PubMed&list_uids=805044&dopt=Abstract

http://www.pathology.vcu.edu/education/endocrine/endocrine/pituitary/diseases.html --- Clomiphene blocks estrogen receptors, this causes GnRH release and elevation of LH. A lack of response may point to hypothalamic dysfunction.

http://www.aarda.org/infocus_article.php?ID=20 -- FSH elevation indicative of autoimmune disease!

LH as a neglected measure:

http://www.ncbi.nlm.nih.gov/entrez/query.fcgi?db=pubmed&cmd=Retrieve&dopt=AbstractPlus&list_uids=16412772&query_hl=2&itool=pubmed_DocSum

August 2006 study showing low reliability of Ovarian Reserve to IVF success rates:

http://www.ncbi.nlm.nih.gov/entrez/query.fcgi?db=pubmed&cmd=Retrieve&dopt=AbstractPlus&list_uids=16891297&query_hl=5&itool=pubmed_docsum

I have to say, I think that the doc's are rather presumptuous to say that they can't treat you. There is a possibility that other factors are at play from reading through the lit. Most doctor's are trying to keep their numbers up http://www.motherjones.com/news/feature/2006/07/breeder_reaction.html It is not easy to diagnose unusual problems.

I have spent the last 12 years keeping up with immunological research because I have severe allergies - not the type most people deal with. I'm part of the 3% who really can die from minimal exposure to an allergen. Research in reproduction is woefully behind several other fields. They are a 'baby' field in more ways than one! You need to find a doctor who knows that. I also have gotten spoiled by some excellent physicians who knew they didn't have all the answers.

For me, I fit 3 of the possible reasons for a high FSH reason that do NOT mean DOR or POR:
-- Familial twinning (mom and her mom are fraternal, plus she has a cousin who had 2 sets of fraternals; father's family one of the rare hereditary monozygotic twinning families.)
-- Taking Cimetidine. (New doc said he only knew about it because he was 'old'.)
-- TSH levels are borderline (4 - new guidelines say a TSH reading must be 1 or 2 to get pregnant.) There is also research (see above) that indicates elevated FSH + borderline TSH are early markers for Hashimoto's disease.) [Now normal (2.1 in June), but I have to wonder if allergy season raised it in me (May in MI)... I'm the 'research' case of allergy.

The new RE is well-known for research and having people who have worked for him go off to open new clinics - or run other clinics. He may not do a lot of IVFs compared to some other clinics, but I am having a real sense that he looks more closely at the case than those who are just looking to keep numbers up.

The High FSH diagnosis, as I do more research, seems more and more a crutch used to keep numbers up. Remember, fertility drugs were not widely used until the late 80s! That was over 10 years with working with just 1 or 2 eggs! Also, I haven't been able to track the study down again, lost it in BSOD, but, it said there is no difference in the number of natural pregnancies by age group when controlling for High FSH. (If anyone finds it, please post so I can add it to my list.)

There is also growing evidence that Ovarian Volume and antral follicle count is a better measure of Ovarian Reserve than any endocrinological test:

"Recent data indicate that the number of antral follicles present on cycle day 3 provides a better single prognostic indicator for poor response during IVF than the patient's age or any other endocrine marker.[58,60] Ovarian volume, which partly reflects the number of ovarian follicles, has also been shown to decrease with age,[61] and several studies have suggested a role for this parameter as a marker of ovarian reserve.[62,63,64] from : http://www.medscape.com/viewarticle/522445_4"

I just started this journey, and, I'm amazed at how little they really know about this most basic human function!

MLO

Source: http://www.network54.com/Forum/209394/message/1159455294/

read more

Monday, April 16, 2007

Standard Infertility Treatment Best for Hormone Disorder

Monday, April 16, 2007
Clomiphene delivers more pregnancies for women with polycystic ovary syndrome, study finds

WEDNESDAY, Feb. 7 (HealthDay News) -- Women with polycystic ovary syndrome who want to have a baby will probably have better luck if they take the fertility drug clomiphene instead of metformin, an insulin-sensitizing medication that helps induce ovulation in women with the disorder.

That's the conclusion of new research that found the live birth rate was 22.5 percent for women taking clomiphene, compared to just 7.2 percent for those on metformin.

"Many people thought that metformin would be more effective, but it failed on two counts -- either alone or in combination with clomiphene," said the study's lead author, Dr. Richard Legro, professor of obstetrics and gynecology at Penn State College of Medicine.

"Clomiphene alone is the gold-standard way for women with PCOS to achieve pregnancy," he added.

The study, funded by the National Institutes of Health, is published in the Feb. 8 issue of the New England Journal of Medicine. Bristol-Myers Squibb provided the metformin and the placebos used in the study.

Polycystic ovary syndrome (PCOS) is a common endocrinological disorder. It affects as many as 8 percent of American women and may be the cause of most infertility, according to background information in the article. Women with PCOS are often overweight, have excess body and facial hair, reduced insulin sensitivity and irregular menstrual cycles. The root of many of these symptoms is an excess of androgens, or male hormones.

Many women with PCOS are treated with metformin (brand name, Glucophage), a diabetes drug that helps increase the body's response to insulin. This, in turn, reduces the levels of circulating insulin, which reduces the levels of androgens. This often helps restore ovulation and normal menstruation, and possibly helps some women lose weight. Many also believe that metformin could help with PCOS-related infertility, according to the article.

Dr. David Guzick is dean of the School of Medicine at the University of Rochester School of Medicine and Dentistry, in Rochester, N.Y. The author of an accompanying editorial in the journal, he said: "Metformin took hold as a generally accepted treatment. The belief was that because you're addressing the underlying abnormality, you're restoring the system back to normal.

"Clomiphene was viewed as old-fashioned and not reflecting the physiology of PCOS. However, this study found the reverse is true, the old-fashioned way is shown to be preferable," he added.

Guzick said clomiphene works more directly than metformin when it comes to fertility. Clomiphene causes the body to release follicle-stimulating hormone, which stimulates the ovaries to release an egg.

For the new study, the researchers recruited 626 women with PCOS who were infertile. The average duration of infertility, according to Legro, was three years.

The women were randomly assigned to receive clomiphene plus a placebo, metformin plus a placebo, or both metformin and clomiphene for as long as six months.

The combination group had the highest live-birth rate with 26.8 percent. The live-birth rate for the clomiphene group was 22.5 percent, while the metformin group's live-birth rate was just 7.2 percent. The difference between the combination group and the clomiphene group was not statistically significant, the researchers said.

While metformin and clomiphene both caused women to ovulate more, Legro said another interesting finding from this study was that "all ovulations are not alike" and that studies like this one can't stop at looking at the ovulation rate but need to follow through to see how many women actually achieve a pregnancy.

Another concern, Legro said, was that more women on metformin experienced first-trimester pregnancy loss. While the numbers weren't statistically significant in the study, Legro said the finding was troubling, and he would recommend that women stop metformin as soon as they know they're pregnant.

The biggest concern with clomiphene is the increased risk of multiple births, according to Legro. In this study, the rate of multiple births in the clomiphene group was 6 percent, compared to zero percent in the metformin group.

The bottom line, said Legro, is that women with PCOS who want to conceive should get clomiphene as their first-line therapy. "Metformin is not as good as it was hyped to be, but this is not the first time a newcomer has been dethroned," he added.

Guzick said that, aside from medication, one of the most important things women with PCOS can do, both to get pregnant and improve overall health, is to lose weight.

"Even losing just five to 10 pounds can lead to a 50 percent increase in ovulation," said Guzick. And, losing weight prior to conception can also help women lower the risk of some pregnancy complications, he said.

Source: http://www.nlm.nih.gov/medlineplus/news/fullstory_45008.html

read more